


You notice a cluster of tiny red bumps on your newborn's cheeks at 11 p.m., and your brain immediately starts running scenarios. Is it an allergic reaction to formula? Heat from the swaddle? Or the beginnings of eczema that will keep everyone awake for weeks? Newborn skin is remarkably delicate, and in the first three months, nearly 70% of infants develop at least one visible skin eruption as their epidermal barrier adapts to life outside the womb.
The challenge for parents is that infant skin conditions frequently mimic one another. A breakout of baby acne looks suspiciously like heat rash to an untrained eye, while early atopic eczema is often mistaken for dry skin or milia. Using a baby skin rash identifier approach—focusing on the age of onset, bump texture, and precise body distribution—allows you to distinguish harmless, self-resolving newborn skin bumps from conditions that require targeted barrier repair or a call to your pediatrician. If you are also tracking other newborn health signals, our guides on newborn jaundice signs on darker skin and umbilical cord care offer clear visual benchmarks for early development.
- Baby acne vs. eczema: Baby acne appears at 2–4 weeks as non-itchy red pustules on the face; eczema starts after 2 months as intensely itchy, dry, scaly patches on flexural folds.
- Milia are not acne: Milia are tiny, pearl-white keratin cysts on the nose and cheeks present at birth that resolve spontaneously within 4 weeks without squeezing.
- Heat rash cools down fast: Pinpoint pink or clear bumps in neck folds and chest clear within 24–48 hours once you remove excess layers and cool the room.
- Darker skin presentation: Inflammation on South Asian, Arab, and Black infant skin often manifests as violaceous (purplish), hyperpigmented, or brownish patches rather than textbook bright red.
Quick Newborn Skin Triage: Comparing the Big 6 Bumps
To identify a baby skin rash accurately, pediatric dermatologists evaluate three primary factors: the child's exact age in weeks, whether the bumps feel rough or smooth, and where the eruption is concentrated. According to the American Academy of Dermatology Association, over 80% of newborn facial rashes are benign, non-infectious, and require minimal intervention beyond gentle cleansing.
| Condition | Typical Age | Primary Location | Texture & Feel | Distinctive Hallmarks | Quick Action |
|---|---|---|---|---|---|
| Baby Acne | 2–6 weeks | Cheeks, forehead, chin | Small firm bumps/pustules | Flushes when crying; zero itching | Wash with warm water; do not squeeze |
| Milia | Birth to 4 weeks | Nose bridge, cheeks, chin | Smooth, hard, pearl-like | Tiny white cysts under surface skin | Leave alone; resolves in 2–4 weeks |
| Baby Eczema | 2–6 months+ | Cheeks, elbows, knees, trunk | Dry, rough, sandpaper-like | Intensely itchy, scaly, red/purplish | Thick emollient cream; avoid fragrance |
| Heat Rash | Any age | Neck creases, chest, back, groin | Tiny prickly bumps or clear droplets | Appears rapidly after sweating/bundling | Cool room, light cotton clothes, dry skin |
| Erythema Toxicum | Day 2 to 2 weeks | Chest, back, face, thighs | Blotchy patches with central dot | Looks like "flea bites"; shifts locations daily | Self-limiting; disappears in 7–14 days |
| Cradle Cap | 3 weeks to 12 months | Scalp, eyebrows, behind ears | Greasy, waxy, thick crusts | Yellow/flaky scales; non-itchy | Gentle oil massage & soft brushing |
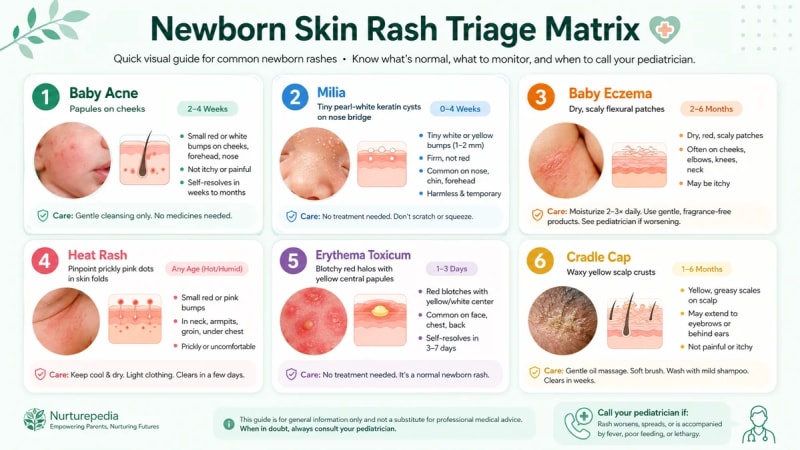
Newborn Skin Rash Triage Matrix: Compare age of onset, bump texture, and facial vs. body location across the 6 most common infant skin conditions.
Baby Acne (Neonatal Cephalic Pustulosis): Red Pox That Peak at 2–4 Weeks
Baby acne—clinically known as neonatal cephalic pustulosis—affects approximately 20% of newborns. It typically emerges between 2 and 4 weeks of age, manifesting as small red papules and tiny white pustules clustered across the cheeks, nose, and forehead. A 2020 pediatric dermatology study in Pediatric Dermatology demonstrated that neonatal acne is driven by maternal hormone stimulation of immature sebaceous glands, combined with skin colonization by Malassezia yeast species, rather than clogged pores from dirt or milk residue.
One defining hallmark of baby acne is its variability throughout the day. When your baby cries, gets warm, or rubs their face against your shirt, the breakout flushes bright red. When they are calm and cool, the redness recedes, leaving faint pimples behind. Crucially, baby acne does not bother your infant—it does not itch, sting, or cause fussiness during feeding.
Management requires patience rather than active medication. Wash the face once daily with lukewarm water and a mild, fragrance-free cleanser. Avoid applying heavy oils, petroleum jelly, or adult acne lotions containing benzoyl peroxide or salicylic acid, which can cause chemical burns on thin infant skin. Baby acne resolves naturally within 6 to 12 weeks without leaving scars.
Milia: Pearl-White Cysts That Need Zero Treatment
Milia appear on up to 50% of full-term newborns, often present at birth or emerging within the first week. These tiny, 1-to-2-millimeter pearly white or yellowish bumps are concentrated across the bridge of the nose, chin, and upper cheeks. Parents frequently ask whether milia are a form of early acne, but their underlying biology is completely different.
The Cleveland Clinic notes that milia occur when dead skin flakes (keratin) become trapped in tiny pockets near the surface of the skin instead of sloughing off. Unlike acne pimples, milia are not inflamed, have no surrounding red halo, and feel smooth and firm to the touch.
The golden rule for milia is strict hands-off care. Never attempt to pop, squeeze, or scrub milia bumps. Squeezing introduces bacteria from your fingers into the tiny pore, transforming a harmless cosmetic spot into a painful staphylococcal skin infection. As the outer skin layer sheds over the first 2 to 4 weeks, the trapped keratin escapes naturally, leaving smooth skin behind.
Baby Eczema (Atopic Dermatitis): Dry, Itchy, Scaly Flares
While baby acne and milia appear in the first month and cause no discomfort, baby eczema (atopic dermatitis) usually surfaces between 2 and 6 months of age and causes intense itching. Eczema is a chronic inflammatory skin condition caused by a compromised epidermal barrier. Research published in JAMA Pediatrics indicates that genetic variations in the filaggrin protein reduce the skin's ability to retain moisture, allowing environmental irritants and allergens to penetrate.
In young infants, eczema begins on the cheeks and forehead before spreading to the outer arms, legs, and chest. The skin feels rough, dry, and coarse—frequently described by parents as feeling like fine sandpaper. Unlike baby acne, eczema patches are scaly, may ooze clear fluid during severe flare-ups, and cause significant infant distress, leading babies to rub their faces against bedsheets or clothing to scratch.
Treating infant eczema requires restoring the lipid barrier. Apply a thick, fragrance-free emollient ointment or ceramide cream within three minutes of lukewarm baths to trap moisture. For detailed flare management strategies, bath routines, and trigger identification, see our comprehensive guide on baby eczema treatments.
Heat Rash (Miliaria): Pinpoint Prickly Pink Bumps in Skin Folds
Heat rash—known clinically as miliaria—develops when immature sweat ducts become blocked, trapping sweat beneath the skin. It can occur at any age but is exceptionally common in newborns during warm weather or when parents over-bundle their baby in synthetic swaddles and heavy sleep sacks.
Heat rash presents as tiny, pinpoint pink or clear fluid-filled bumps concentrated in places where heat and friction accumulate: the neck folds, armpits, chest, back, and upper thighs. If the blockage occurs shallowly in the epidermis (miliaria crystallina), it looks like clear water droplets. If it occurs deeper (miliaria rubra), it forms itchy, prickly red dots.
Resolving heat rash requires cooling the skin rather than applying heavy salves. Remove excess clothing layers, switch to breathable 100% organic cotton fabrics, keep the nursery temperature between 68°F and 72°F (20°C–22°C), and give your baby a cool sponge bath. Avoid thick ointments like petroleum jelly on active heat rash, as heavy creams further block the sweat ducts. Heat rash typically fades within 24 to 48 hours once the baby cools down.
Erythema Toxicum Neonatorum: Flea-Bite Blotches That Shift Daily
Despite its alarming medical name, erythema toxicum neonatorum (ETN) is a completely benign condition affecting up to 50% of healthy full-term infants. It typically appears between day 2 and day 5 of life, though onset can occur up to 2 weeks postpartum.
ETN creates blotchy red patches ranging from a few millimeters to several centimeters across, with a small yellow or white bump (papule) in the center. The appearance closely resembles small flea bites. What sets ETN apart from other rashes is its rapid movement: a red patch on the chest at breakfast may fade by afternoon, only for new blotches to appear on the back or thighs by evening.
According to AAP HealthyChildren guidance, ETN causes no systemic illness, fever, or discomfort. The bumps contain eosinophils (a type of white blood cell) responding to the skin's exposure to microbes outside the womb. No treatment is necessary; ETN resolves entirely on its own within 7 to 14 days without residual marks.
Cradle Cap (Seborrheic Dermatitis): Waxy Yellow Scalp Scales
Cradle cap (infantile seborrheic dermatitis) is the scalp equivalent of baby acne. Emerging between 3 weeks and 3 months of age, it manifests as greasy, yellow or brownish waxy crusts and flaky scales across the crown of the head, eyebrows, behind the ears, and occasionally along the sides of the nose.
Cradle cap is caused by overactive oil glands producing excess sebum, which traps shedding skin cells. While the thick scales look uncomfortable, cradle cap is non-itchy and does not disturb the baby. To clear build-up safely, massage a small amount of plant-based oil into the scalp 15 minutes before bath time, wash with a mild baby shampoo, and gently loosen scales using a soft silicone scalp brush. For a complete walkthrough on safe scalp care, read our step-by-step cradle cap treatment guide.
Cradle Cap Treatment: Causes, Safe Scalp Remedies, and Timeline
Rash Identification on Darker & Melanated Infant Skin
Most medical textbooks illustrate infant skin rashes exclusively on fair skin tones, describing erythema as "bright red" or "rosy pink." For South Asian, Arab, Middle Eastern, Black, and brown infants, vascular responses present differently due to higher baseline melanin density in the upper dermis.
On melanated skin, inflammatory conditions like eczema, heat rash, or erythema toxicum often appear violaceous (purplish), deep brown, dark pink, or hyperpigmented. Eczema patches may look like raised grayish-brown bumps rather than bright red scaling. Similarly, post-inflammatory hyperpigmentation—temporary darkening of the skin where a rash healed—is common on brown infant skin and can persist for several weeks after the underlying inflammation has resolved.
When assessing skin rashes on darker skin tones, rely heavily on tactile feedback (roughness, swelling, heat) rather than color alone. Gently touch the area: if the skin feels significantly warmer than surrounding areas, swollen, or rough like sandpaper, active inflammation is present regardless of whether you see bright redness. For parents navigating skin tone nuances, our visual guide to newborn jaundice on darker skin provides additional visual evaluation criteria.

Tactile & Visual Evaluation on Darker Skin: Inspecting subtle violaceous (purplish) or hyperpigmented inflammatory patches under natural daylight.
Cultural Remedies vs. Evidence-Based Infant Skin Care
In many South Asian, Middle Eastern, and immigrant communities, newborn skin bumps prompt immediate advice from grandmothers and aunts advocating traditional remedies: raw mustard oil massages, turmeric (haldi) pastes, herbal ubtan scrubs, or ghutti preparations. While rooted in care, several of these traditional practices can severely aggravate a newborn's compromised skin barrier.
Clinical dermatological studies, including research published in the British Journal of Dermatology, have shown that unrefined mustard oil has a high oleic acid content that damages the stratum corneum, increases transepidermal water loss, and intensifies eczema flares. Herbal pastes and coarse ubtan scrubs introduce physical friction and potential allergen sensitivities to inflamed skin, increasing the risk of secondary bacterial infections.
Safely bridging cultural tradition with modern pediatric science means selecting evidence-backed alternatives. If your family prefers natural oils for infant massage, choose cold-pressed sunflower seed oil or pharmaceutical-grade coconut oil, both of which contain high linoleic acid concentrations that strengthen the skin barrier. For daily cleansing, adhere to gentle, fragrance-free routines outlined in our guide on proper newborn bathing techniques.

Infant Skin Barrier Care: Choose linoleic acid-rich oils and ceramide emollients; avoid raw mustard oil or abrasive herbal ubtan scrubs on compromised skin.
Contact your pediatrician or seek immediate urgent care if your baby's rash is accompanied by a fever of 100.4°F (38°C) or higher in an infant under 3 months, extreme lethargy, poor feeding, or if the rash consists of non-blanching purple spots (petechiae) that do not fade when pressed firmly with a clear glass tumbler. Fluid-filled blisters or open, weeping sores with honey-colored crusts require prompt evaluation for viral (HSV) or bacterial (impetigo) infection.
When to Worry: Red Flag Symptoms That Require Immediate Care
While the vast majority of newborn skin bumps are benign, certain skin signs indicate serious systemic infections or dermatological emergencies. Parents should monitor for five specific red flag indicators:
- Fever + Rash in Infants Under 3 Months: Any rectal temperature of 100.4°F (38°C) or higher paired with a new rash requires emergency evaluation to rule out neonatal sepsis or viral encephalitis.
- Non-Blanching Petechiae/Purpura: Tiny pinpoint purple or dark red dots that do not momentarily turn white when pressed (the "glass tumbler test") can signal meningococcal disease or blood clotting disorders.
- Fluid-Filled Blisters (Vesicles): Clusters of clear blisters, especially on the scalp, mouth, or eyes in the first 4 weeks, can indicate neonatal Herpes Simplex Virus (HSV-1), which is a medical emergency.
- Honey-Colored Crusting or Weeping Pus: Open lesions that ooze yellowish fluid and form sticky golden crusts point to impetigo (staph or strep infection) requiring topical or oral antibiotics.
- Rapid Spreading with Irritability: A rash that spreads rapidly across the entire body within hours, accompanied by persistent crying, refusal to feed, or swelling of the face/lips, demands urgent care.
If your baby is dealing with skin irritation localized to the diaper region that is not clearing with standard barrier creams, see our guide to stubborn diaper rash and yeast infections for targeted treatment protocols.
Sources & Clinical References
- American Academy of Dermatology Association (AADA) — Caring for Your Baby's Skin
- American Academy of Pediatrics (HealthyChildren.org) — Common Newborn Rashes
- Pediatric Dermatology — Pathophysiology of Neonatal Cephalic Pustulosis and Sebaceous Gland Maturation (2020)
- JAMA Pediatrics — Epidermal Barrier Integrity and Early Onset Atopic Dermatitis in Infants (2020)
- Cleveland Clinic — Milia in Newborns: Symptoms, Causes & Removal
- British Journal of Dermatology — Effect of Topical Oils on Neonatal Skin Barrier Function (2011)
This article is for informational purposes only and does not constitute medical advice. Always consult your pediatrician or pediatric dermatologist for diagnosis and treatment of persistent, worsening, or systemic infant skin conditions.
From ovulation tracking and due dates to baby names and growth charts. Everything you need for your journey.
Share this post
Frequently Asked Questions
Related Topics
Explore More in Baby Care & Health
Newborn care basics, pediatric symptom checks, and daily infant wellness.
Found this useful?
Tell Google to show you Nurturepedia more often. It takes one tap and applies across Search and AI results.





